
Florida Central Line Errors That Cause a Punctured Lung
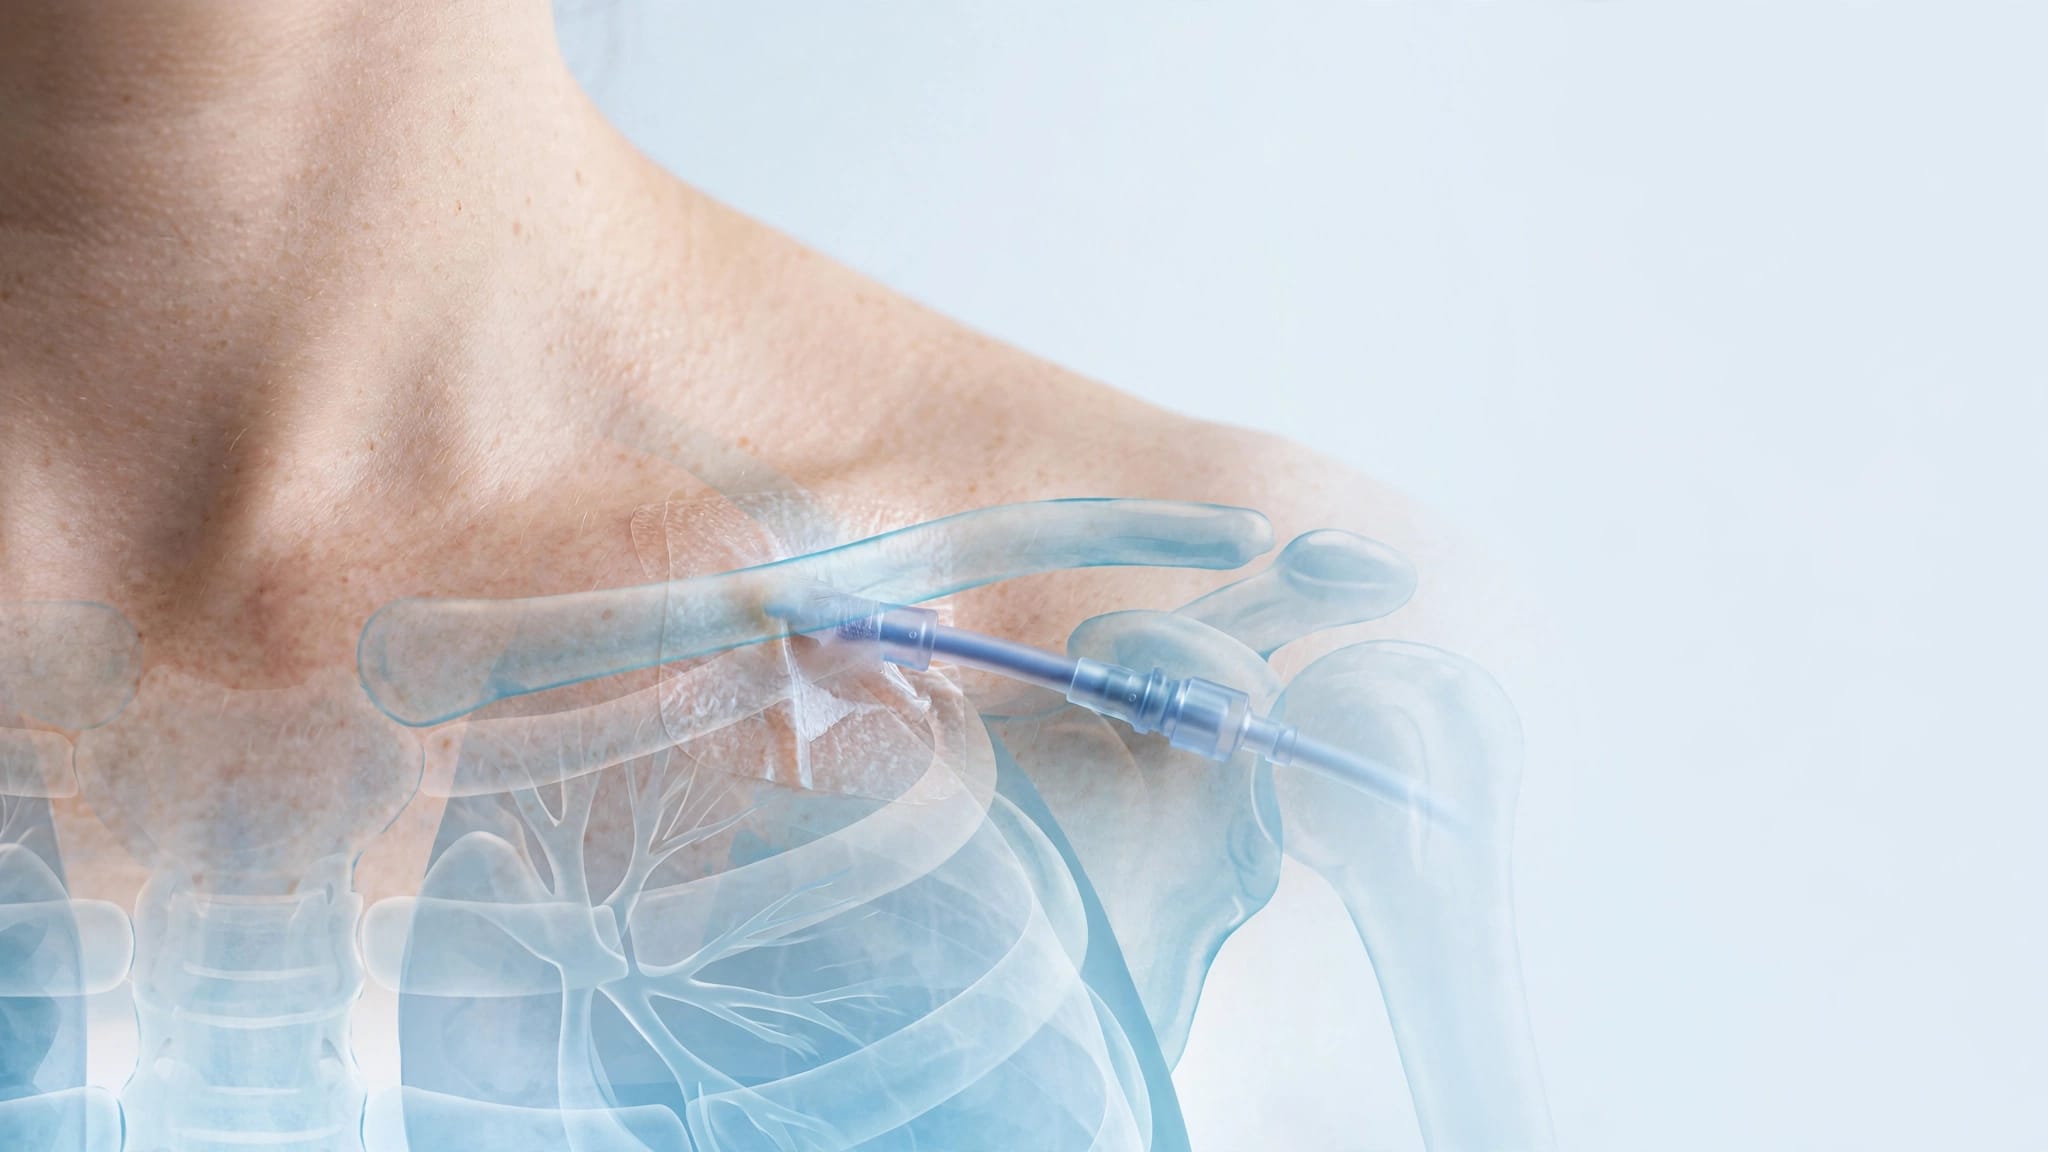
A central line can puncture a lung when an insertion needle injures nearby pleura or lung tissue. A Florida central line injury may support a malpractice claim when negligent placement or follow-up care causes preventable harm.
If you’ve needed a chest tube or additional hospitalization, the medical timeline helps distinguish a recognized complication from negligent care. The review starts with how the injury occurred and how the care team responded.
Key Takeaways
- A punctured lung after central-line placement doesn’t automatically establish malpractice.
- A review may examine needle technique, ultrasound use, repeated attempts, and the response to breathing problems.
- Medical records and qualified expert analysis must connect substandard care to injury.
- Florida requires presuit investigation and notice, and filing deadlines can run while treatment continues.
How Central-Line Placement Can Injure a Lung
A central venous catheter, or CVC, provides access to a large vein for medications, fluids, or other treatment. When clinicians use a neck or upper-chest approach, the insertion site is close to the lung.
Needle depth and repeated attempts
The access needle can pass through the back wall of a vein or travel in the wrong direction. If it damages the pleura or lung, air can collect between the lung and chest wall. This condition, called a pneumothorax, can cause partial or complete lung collapse.
Repeated unsuccessful punctures create additional opportunities for injury. A medical review considers why attempts continued, whether the clinician reassessed the approach, and whether additional assistance or another technique was appropriate.
Ultrasound guidance and site selection
The CDC’s central-catheter placement guidance recommends ultrasound, when available, to reduce insertion attempts and mechanical complications. Clinicians must also have appropriate training in its use.
However, ultrasound doesn’t eliminate every risk. Site selection also requires balancing competing concerns. For example, subclavian access may offer infection-prevention benefits for certain adult catheters but carries mechanical risks, including pneumothorax. An expert evaluates the patient’s anatomy and treatment needs rather than assuming one insertion site was always required.
Symptoms That Need Prompt Medical Attention
New shortness of breath, chest pain, or coughing after central-line placement warrants prompt assessment. A falling oxygen level or increasing need for breathing support can also signal a problem.
If you’re hospitalized, alert a nurse or physician immediately. After discharge, call 911 for severe breathing difficulty, fainting, or severe chest pain. Don’t postpone emergency care while considering a legal claim.
A pneumothorax can enlarge after the procedure. In a tension pneumothorax, pressure builds enough to threaten breathing and circulation, so emergency treatment is necessary.
Treatment depends on the patient’s condition and the size and progression of the air collection. Some patients need observation or supplemental oxygen; others need drainage, including a chest tube. The fact that treatment became necessary establishes an injury, but it doesn’t identify whether anyone acted negligently.
When a Florida Central Line Injury Supports a Claim
A malpractice claim needs evidence of a professional duty, substandard care, a causal connection, and resulting losses.
Establishing a departure from accepted care
Florida evaluates treatment against what reasonably prudent, similarly qualified providers would do under comparable circumstances. Our explanation of the Florida medical malpractice standard addresses that comparison.
For central-line injuries, an expert may examine needle direction, insertion depth, operator training, or the decision to continue unsuccessful attempts. The review also considers the urgency of the procedure and the patient’s condition.
A hospital policy or CDC recommendation can inform that analysis. However, a policy violation alone doesn’t establish every element of a legal claim.
Connecting the failure to preventable harm
The patient must show that negligent care more likely than not caused or worsened the injury. Timing alone isn’t enough, because pneumothorax can occur despite appropriate technique.
The same requirement applies to delayed diagnosis. An expert must determine whether earlier assessment and treatment probably would have reduced the harm.
Even when insertion met the standard of care, negligent follow-up may support a claim if timely treatment probably would have prevented additional injury.
The analysis must also account for preexisting lung disease and other conditions that affected the patient’s recovery.
Medical Records That Help Explain What Happened
The most useful evidence usually establishes a sequence: the patient’s condition before placement, the procedure itself, the first warning signs, and the response.
Procedure notes and imaging
The central-line procedure note may identify the insertion site, clinician, number of attempts, and use of ultrasound. It may also document difficulties or an immediate complication.
Chest imaging helps establish catheter position and the presence or progression of pneumothorax. Reviewers may need the actual images as well as the radiology reports.
Records from before the procedure also matter. Prior chest imaging and respiratory assessments can help distinguish a new injury from an existing condition. Missing or inconsistent documentation raises questions, but it doesn’t replace proof of negligence.
Nursing records and response times
Nursing assessments, oxygen readings, and medication records can show when the patient’s condition changed. Orders and treatment timestamps may reveal how quickly the team reassessed breathing problems or arranged drainage.
Preserve discharge instructions and bills. Also write down when symptoms started, whom you notified, and what response you received. Separate what you personally observed from what someone later told you.
An attorney and medical expert can compare those details with the chart. That comparison may help identify whether a delay occurred and whether it affected the outcome.
Who May Be Responsible for the Injury?
Central-line placement generally involves medical malpractice rather than ordinary negligence because evaluating the alleged failure requires professional medical judgment.
Potential responsibility depends on who controlled the care. The clinician who inserted the line may face different allegations than a provider responsible for interpreting imaging or responding to deterioration. Hospital liability requires its own factual and legal analysis.
Employment relationships and independent-contractor arrangements can affect whether a hospital is responsible for another provider’s conduct. The hospital’s own staffing or supervision decisions may also matter when evidence connects them to the injury.
Participation in treatment doesn’t make every provider liable. In addition, government-connected facilities and certain emergency-care circumstances can involve special notice requirements or liability rules. Identifying the correct parties early helps avoid procedural problems later.
Florida’s Presuit Requirements and Filing Deadlines
Florida medical-negligence claims involve steps that usually must occur before filing a lawsuit. Those steps take time.
Investigation, expert support, and notice
Under Florida’s presuit investigation statute, a claimant generally needs an investigation supported by a qualified medical expert’s verified written opinion. The opinion must corroborate reasonable grounds to believe negligence caused injury.
After investigation, the claimant must notify each prospective defendant before suing. Florida’s medical-negligence notice requirements generally provide a 90-day period during which suit cannot proceed while the recipient investigates.
A complaint to hospital administration doesn’t replace statutory notice. Likewise, an internal hospital review doesn’t satisfy the claimant’s presuit obligations or resolve whether a viable claim exists.
The two-year period and outside deadline
Under Florida’s medical malpractice filing deadlines, claims generally must begin within two years of the incident or its discovery, including when discovery should have occurred through due diligence.
An ordinary four-year statute of repose runs from the incident itself. Exceptions and presuit timing rules can affect the calculation, so a general description isn’t a case-specific deadline.
Continuing treatment, waiting for records, or pursuing a hospital grievance doesn’t automatically preserve a claim. Early legal review allows time to investigate both the injury and the applicable filing requirements.
Compensation Depends on the Harm Negligence Caused
A successful claim may seek compensation for additional medical expenses, lost earnings, and supported future treatment needs. Recoverable damages may also include pain, suffering, and limitations on daily activities where Florida law permits.
For a central-line pneumothorax, the evidence may address chest-tube treatment, additional hospitalization, or a prolonged recovery. However, the claim must separate those losses from care the underlying illness would have required anyway.
Documented work restrictions and medical opinions about future limitations can affect the damages analysis. No settlement amount follows automatically from a diagnosis or procedure.
If the patient dies, a wrongful death claim may be available. Florida law determines who may bring that claim and which losses qualify for recovery.
Frequently Asked Questions
Does signing a consent form prevent a claim?
A signed consent form doesn’t automatically defeat a negligence claim. Consent to a recognized complication and proof that a provider used appropriate care are separate issues.
However, the occurrence of a disclosed complication doesn’t itself establish negligence either. The review still examines how the procedure occurred and whether substandard care caused injury. An informed-consent allegation also raises different questions from an allegation about insertion technique.
What if the first chest X-ray was normal?
A normal immediate chest X-ray doesn’t necessarily exclude a small or developing pneumothorax, particularly when the patient was lying flat. Later symptoms may require reassessment despite an earlier reassuring image.
For a legal claim, an expert considers what information providers had at each decision point. The issue is whether their response met the applicable standard and whether any delay probably caused additional harm.
Protecting Your Options After a Central-Line Injury
A punctured lung deserves careful review when unsafe placement or a delayed response may have caused preventable harm. The strongest analysis connects the treatment timeline with qualified medical evidence and documented losses.
Continue necessary care and preserve available records. Seek legal advice promptly rather than waiting for recovery or a hospital’s internal decision.
At Avard Law Offices, we offer a free consultation to discuss your injury and legal options.